The sildenafil + dapoxetine combination: what the trials measured, and what they left out
A randomised five-arm trial in 150 men with premature ejaculation put the combination first on latency, satisfaction and the diagnostic tool — but used single-blind design with no placebo blinding across arms. The 2019 open-label study reported latency rising from 22.72 to 68.25 seconds with no comparator at all. This page reads what the evidence actually measured.
19 October 2026 · 4 min read
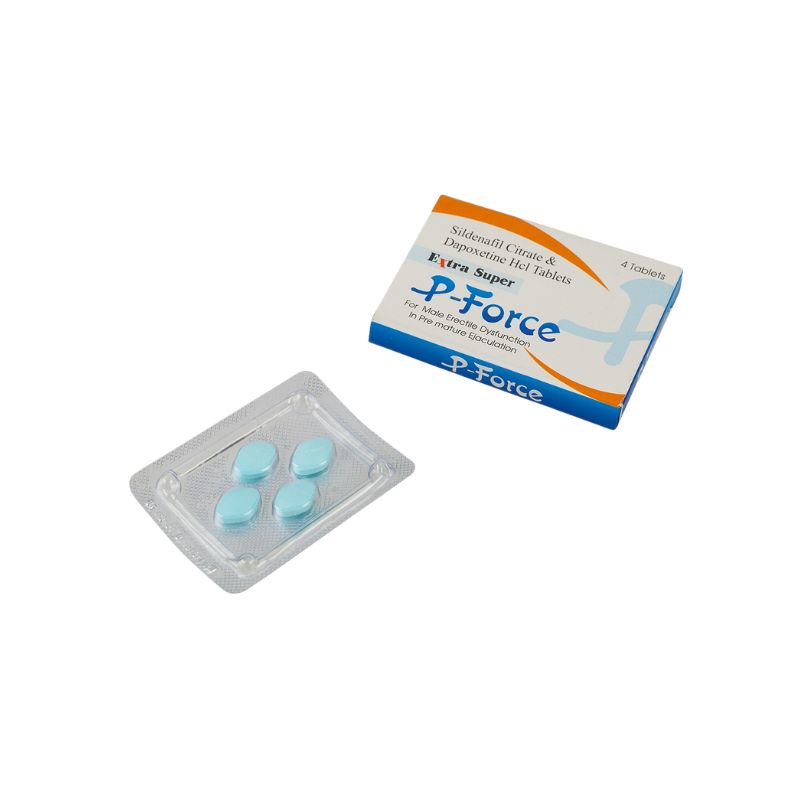 Extra Super P-Force (Sildenafil + Dapoxetine)
A fixed-dose tablet of a short-acting SSRI next to a PDE5 inhibitor is one of the few genuinely interesting pharmacology stories in this catalogue, because the two drugs address different halves of the same clinical problem. It is also, on the evidence available, one of the thinner ones. This page reports what the trials measured and what they left out.
The five-arm comparison
The 2018 randomised study is the most informative design on this subject. It enrolled 150 men with premature ejaculation and without erectile dysfunction, randomising them to five groups of 30: on-demand placebo, paroxetine 30 mg, dapoxetine 30 mg, sildenafil citrate 50 mg, and dapoxetine 30 mg combined with sildenafil 50 mg, each for six weeks. Patients recorded intravaginal ejaculatory latency time and completed the Premature Ejaculation Diagnostic Tool and a satisfaction score before and after.
Latency, satisfaction and PEDT improved significantly in all groups (p = .001), and the combination group had the best values on all three (p < .001).
Two things in the design matter. It was single-blind — participants were randomised but not blinded to what they were taking, which is a substantial problem when the endpoint is a stopwatch and a questionnaire. And there is no placebo-versus-combination comparison in the abstract’s framing of the result: the combination is ranked against the other active arms, so the effect attributable to the combination itself is not separated from the effects of its two components.
The open-label study, and its latency numbers
The 2019 DAP-SPEED study is the one usually quoted for the combination tablet, and it is a single-centre, single-arm, open-label design: 74 patients with lifelong or acquired premature ejaculation and concomitant erectile dysfunction, treated on demand for four weeks, with 53 completing.
Reported changes were geometric mean IELT from 22.72 ± 15.16 to 68.25 ± 82.33 seconds (p < 0.001), PEP index improving from 0.86 ± 0.72 to 2.36 ± 1.13, and IIEF-EF from 13.17 ± 3.33 to 24.60 ± 3.96 (both p < 0.001). 81.13% of patients were satisfied on the global impression of change. Non-serious adverse events occurred in 10 patients (18.87%) and four (7.55%) dropped out; the most common adverse events were headache, palpitation and flushing.
Look at the standard deviations on the latency figures: 15.16 seconds before and 82.33 seconds after, on a mean of 68. That is a distribution with a very long right tail, in an uncontrolled design. It supports the statement that latency increased in this group of patients. It does not support a controlled effect size.
The interaction study, which is the most useful one here
The 2006 open-label randomised crossover study in 24 men is the cleanest pharmacokinetic data on the pair. Participants received dapoxetine 60 mg alone, dapoxetine 60 mg with tadalafil 20 mg, or dapoxetine 60 mg with sildenafil 100 mg. Tadalafil did not affect dapoxetine pharmacokinetics; sildenafil increased the dapoxetine AUC by 22%, which the authors deemed not clinically important. Dapoxetine did not affect the pharmacokinetics of tadalafil or sildenafil. Most adverse events were mild.
That is a clean answer to the question the combination products raise: there is no meaningful pharmacokinetic interaction between the two classes.
The comparator people forget
The 2023 meta-analysis of topical anaesthetics in premature ejaculation pooled 11 randomised controlled trials with 2,008 participants and compared them across interventions. It found lidocaine gel more effective than paroxetine or sildenafil (P = 0.04 and P < 0.00001 respectively), and concluded that topical anaesthetics increase IELT more effectively than placebo, sildenafil, tadalafil, paroxetine and dapoxetine.
It is a different class of intervention, with its own downsides, and this page is not arguing for it. The point is narrower: on the one endpoint that gets measured in this literature — latency — a non-drug option outranked both single agents in pooled randomised data.
What the data do not show
They do not show a blinded, placebo-controlled efficacy trial of a fixed-dose combination. The best design available is single-blind with an active comparator, and the flagship open-label study has no comparator.
They do not show a separate contribution for each component. The five-arm trial ranks the combination above each drug alone, which is a ranking rather than a decomposition.
They do not show a cardiovascular outcome, or a safety profile at scale. The interaction study is 24 men and open-label.
They do not show durability. The longest duration on this page is six weeks of treatment in the randomised arm and four weeks in the open-label study.
Where this sits on the shelf
The compounds as supplied by the manufacturer: Extra Super P-Force (Sildenafil + Dapoxetine) · P-Force (Sildenafil + Dapoxetine) · Super Carefill (Tadalafil + Dapoxetine)
What we supply
The combination preparations above, as supplied by the manufacturer, tracked, from inside the EU.
Research use only. This page summarises published studies for research reference. It is not medical advice, not a protocol, and not a suggestion for human use. Nothing we supply is for human or veterinary use.
References.
- Abu El-Hamd M, et al. Comparison of the clinical efficacy and safety of the on-demand use of paroxetine, dapoxetine, sildenafil and combined dapoxetine with sildenafil in treatment of patients with premature ejaculation: A randomised placebo-controlled clinical trial. Andrologia 2018;50(1).
- Tuken M, et al. Efficacy and safety of dapoxetine/sildenafil combination tablets in the treatment of men with premature ejaculation and concomitant erectile dysfunction-DAP-SPEED Study. Int J Impot Res 2019;31(2):92-96.
- Dresser MJ, et al. Dapoxetine, a novel treatment for premature ejaculation, does not have pharmacokinetic interactions with phosphodiesterase-5 inhibitors. Int J Impot Res 2006;18(1):104-110.
- Shah MDA, et al. Topical Anesthetics and Premature Ejaculation: A Systematic Review and Meta-Analysis. Cureus 2023;15(8):e42913.
- Wang WF, et al. Selective serotonin reuptake inhibitors in the treatment of premature ejaculation. Chin Med J (Engl) 2007;120(11):1000-1006.